
This FAQ contains questions not answered in the Process Details document. Please review this document if your questions are not answered below.
FAQ Last Updated: 10/26/2026
Click on a question below to display the answer.
General
Yes, residential providers will be required to complete data submissions each year as a part of Performance-Based Contracting. PBC data collection occurs during the months of February and March each year.
The measures will progress with the goal of improving services for individuals and families. Small changes will be made from year to year. Larger changes will happen every 3 years.
Yes, all providers of residential services through the Consolidated and Community Living Waivers are required to submit for tier determination, regardless of the tier for which they meet the criteria.
Providers should only apply for the tier for which they know they meet the required measures. CAPs will not be used in this manner.
Effective January 1, 2025, when ODP determines that there is a need for additional Residential Habilitation, Life Sharing, or Supported Living providers, new residential provider applicants will be invited to qualify for enrollment through a competitive request for application process.
In the meantime, we strongly encourage applicants to enroll to provide non-residential services to gain the experience necessary for successful residential service provision. Experience serving individuals with intellectual disabilities and autism will be a factor considered in the selection of new residential provider applicants through the competitive request for application process.
This only applies to providers that are not enrolled and qualified to provide Residential Habilitation, Life Sharing, or Supported Living services in the Consolidated and/or Community Living Waivers by December 31, 2024.
MyPBC Portal
MyPBC Portal will open to receive PBC submission forms from mid-February to mid-March annually. Submissions will only be received during this window.
Performance-Based Contracting only applies to Residential Habilitation, Life Sharing, and Supported Living services provided through the Consolidated and Community Living Waivers.
Providers should only include information for individuals receiving one of these services and staff involved in the provision of one or more of these services through the Consolidated and Community Living Waivers.
The average time to complete a PBC submission varies by tier. Average times based on tier are:
– Primary = 2 hours
– Select = 3 hours
– Clinically Enhanced = 3 hours
Users do not have to complete an entire submission in one sitting. MyPBC Portal allows users to enter data, save and exit the system, then log in at a later time to finish. A user may return to the submission as often as needed until the deadline for the submission window closes.
Yes. MyPBC Portal does not allow users to complete a submission without answering all required questions. If a user does not complete a mandatory question (indicated by a red asterisk) or navigates away from a page without saving, they will be prompted with a red error message or confirmation pop-up. Some questions have rules on what types of characters users can enter or file upload requirements. Users will see a red error message if they enter a response that does not meet requirements.
Data on the My PBC Profile page is sourced directly from other ODP systems (e.g., HCSIS). If your agency disagrees with the outcome of an ODP data measure, you may use the PBC Resolution Process to submit information that supports your position. Please review the FAQ titled “What is the PBC Resolution Process?” for further information.
It depends. Providers are highly encouraged to review measures and process details year after year, to identify any modifications made to an existing measure. If your agency’s submission passed in the previous PBC review period, and the measure remains unchanged, it is probably appropriate to resubmit the same document.
However, many PBC measures will be modified year after year as part of continuous quality improvement (CQI), so careful review is suggested when measures are released for the next PBC review period to ensure you are prepared to meet them.
All previously unmet measures should be reviewed to identify potential process improvements, and the corresponding documentation should be updated as necessary to ensure compliance in the next PBC review period.
PBC submissions that are successfully received by ODP will have a status of “Completed” on the My PBC Profile screen within MyPBC Portal.
Providers should navigate to the My PBC Profile screen to review the column titled “PBC Submission Status” and confirm it shows a status of “Completed.” Designated MyPBC Portal users will also receive a confirmation email after ODP receives the completed PBC submission.
After ODP receives the submission, the information will be reviewed and ODP determines the measures the provider has met. The agency will receive written notification of their PBC determination once all determinations have been made.
The PBC Resolution Process is an optional activity available to Select and Clinically Enhanced tier submitters that occurs after PBC determination letters have been distributed by ODP. Primary providers are not able to submit for Resolution.
This process allows provider agencies who believe their determination should be amended the opportunity to submit information to ODP supporting their position. This is not an opportunity to correct an unmet measure or submit brand new documentation.
Upon receipt of the agency’s materials, the Department will reexamine its findings, and the agency will be notified in writing regarding the updated determination, including measure(s) evaluations that were changed or remained the same based on the information submitted.
Composite Scoring
Composite scoring is an approach that groups multiple measures together to be scored holistically. Providers pass a composite group by achieving the passing threshold established by ODP for that composite group. For example, if a composite group contains four measures and a provider is required to score 75% to pass, they must meet three of the four measures. The passing threshold will vary by composite group.
Providers can reference the Process Details documentation to review the column labeled “Composite Category” which identifies whether a measure is part of a composite group
Below are explanations for each type of composite listed:
– Not Applicable (NA) – The measure stands alone and is not part of a composite. Providers must meet each of these measures in order to obtain the desired tier.
– Complex Needs (CN) -The measure is part of the Complex Needs composite. Providers must achieve at least 70% of the measures in this category.
– Data to Outcomes (DO) -The measure is part of the Data to Outcomes composite. Providers must achieve at least 80% of the measures in this category.
– Incident Management (IM) -The measure is part of the Incident Management composite. Providers must achieve at least 70% of the measures in this category.
Yes. As an example, to meet Clinically Enhanced – Dual Diagnosis there are 8 measures in the Data to Outcomes (DO) composite. Providers will need to meet at least 7 of the 8 measures in the Data to Outcomes composite to meet Clinically Enhanced – Dual Diagnosis requirements. None of the 7 measures count more than another.
If your agency is submitting for the Clinically Enhanced tier, you can determine whether a given measure is applicable to your submission by reviewing the “Applicability” column of the Data Dictionary:
– ALL (Applies to all tiers)
– C (Applies to Clinically Enhanced only)
– SC (Applies to Select and Clinically Enhanced)
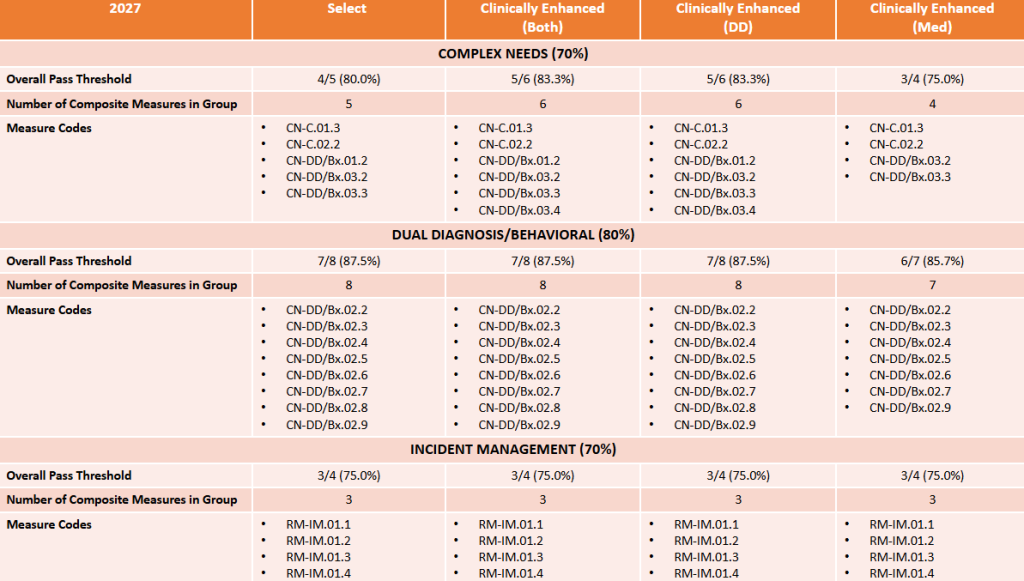
If you cross-reference the Composite Categories for the measures that apply to ALL, C, and SC, you will note that:
– CN has 6 measures.
– DO has 8 measures.
– IM has 4 measures.
To meet or exceed the thresholds for each Composite Category, a provider that is applying for an advanced tier must meet at least:
– 70% of the CN measures, and
– 80% of the DO measures, and
– 70% of the IM measures.
Additionally, all Clinically Enhanced providers must fall into one of the following categories:
– Clinically Enhanced for Medical,
– Clinically Enhanced for Dual Diagnosis, OR
– Clinically Enhanced for Medical & Dual Diagnosis
You will note that each measure that applies to the Clinically Enhanced tier has one of the following codes in the “Clinically Complex Category” field:
– NA
– DD
– MS
To be Clinically Enhanced for Medical, the provider must meet:
– All “NA” measures / composite measures
– CN-M.01.1
But does not have to meet:
– CN-DD/Bx.01.2
– CN-DD/Bx.02.8
– CN-DD/Bx.03.4
– CN-DD/Bx.04.1
To be Clinically Enhanced for Dual Diagnosis, the provider must meet:
– All “NA” measures / composite measures
– CN-DD/Bx.01.2
– CN-DD/Bx.02.8
– CN-DD/Bx.03.4
– CN-DD/Bx.04.1
But does not have to meet:
– CN-M.01.1
To be Clinically Enhanced for Medical and Dual Diagnosis, the provider must meet:
– All “NA” measures / composite measures
– All “DD” measures/composite measures
– All “MS” measures/composite measures
The composites still apply within each category.
Performance Measures: Access
A provider referral is the process by which the SC connects an individual in need of residential services with qualified providers. At minimum, each referral must include the identified service type, summary of medical and behavioral supports needed, and the ISP with PII redacted unless consent is given.
Performance Measures: Administration
Residential providers will be required to submit financial statements (audited if available) each year as part of the Performance-Based Contracting tier determination process. Guidance for the submission is as follows:
– If your agency had a financial audit completed within the past 12 months, submit copies of this audit.
– If your agency did not have an audit completed, submit current financial statements (at minimum profit/loss statements AND balance sheets) reflective of your most recently completed fiscal year.
The term “officer” includes any person who is part of the governing body or appointed to manage the agency as an agent of the governing body. The term includes, but is not limited to, board members, President, Vice President, Chief Operations Officer, Chief Financial Officer, Treasurer, and Secretary. Residential providers will be required to disclose the history and status of criminal convictions of officers and owners on an annual basis for compliance with performance measures.
Performance Measures: Supporting Individuals with Complex Needs
Please review the Process Details for an up-to-date list of accepted clinical staff.
This measure solely applies to the Clinically Enhanced tier. Providers submitting for the Clinically Enhanced tier are not required to report this information. This information will be calculated by ODP as outlined in the Process Details.
The following is an example of how a provider could use HRST to measure daily interruptions:
The provider may notice that people are often having interruption to daily activities due to becoming sick with influenza or other contagious diseases. The provider could discuss with their healthcare team ways to help reduce the likelihood of influenza, and based on recommendations, implement training on proper hand washing techniques or increase awareness of and participation in flu vaccination and therefore reduce number of interruptions in daily activities due to influenza in the future.
As a reminder, “clinical issues” is a discrete metric in HRST.
An equivalent basic course on effectively supporting individuals with Autism Spectrum Disorder must cover the following topics:
– The core deficits in individuals with autism. Co-occurring mental and physical conditions, as they present in individuals with autism. How deficits can change dependent on the environment, daily routines/activities, trauma, medical/psychiatric presentations, and/or supports present/absent in a person’s life.
– Basic information about Applied Behavioral Analysis, including common terms, basic principles used to change behavior and teach new skills. An overview of the process and use of Functional Behavioral Assessments to drive the development and implementation of a Behavioral Support Plan.
– Information on identifying and teaching adaptive skills used in everyday life, the importance of adaptive and independent living skills, and challenges that may arise when teaching adaptive skills to individuals with autism.
– Community engagement, including how community engagement plays a role in supporting individuals with autism and their families. Information about how to best support participants in making informed choices and decisions, while also being aware of the dignity of risk.
– How to support participants in finding and maintaining meaningful employment and educational opportunities. This includes the benefits of employment and postsecondary education in a participant’s life, available vocational and educational supports, and the impact of employment on benefits.
– Information on the basic social and communication deficits associated with autism, and challenges individuals with autism may have in navigating social relationships. Methods that can be used to help individuals improve their social skills. Recognition of the differences in language and communication.
As outlined in the attestation, the provider is expected to produce documentation demonstrating the Residential Provider meets the requirements for all items checked upon request by ODP.
Program managers are staff who oversee and coordinate the operations and activities in one or more residential homes. Program managers include program specialists, house managers, or other agency supervisory or management staff with DSPs and/or FLSs in their chain of command. Due to the importance of this training, ODP encourages providers to have all staff complete training on Autism Spectrum Disorder (i.e., SPeCTRUM or equivalent basic course on effectively supporting individuals with Autism Spectrum Disorder).
Behavioral support hours are hours spent on activities outlined in the behavioral support service definition in the Consolidated and Community Living Waivers. Behavior support staff are staff (employed or contracted) who meet the residential provider qualification requirements in the Consolidated and Community Living Waivers for behavioral specialists.
While there are varying definitions of polypharmacy, the term typically refers to the simultaneous use of multiple drugs (such as 5 or more) by a single individual for one or more conditions, or multiple drugs used by an individual for a single ailment or condition. Since this measure is evaluated by providers’ description of the use of data to impact individual outcomes over time based on measurable factors, the provider may determine how they define polypharmacy as part of their submission to ODP.
This measure applies to the Select and Clinically Enhanced tiers. Training and activities to support trauma-informed care for individuals with intellectual disabilities or autism are any trainings or activities that raise awareness of trauma and its impact on development, the establishment of safe environments, emotional regulation techniques, and building trust between individuals and caregivers.
The following is not an exhaustive list but a few examples of the many resources available to meet this measure, including Health Care Quality Units (HCQUs), HEAL PA, and the Office of Mental Health and Substance Abuse Services (OMHSAS).
– MyODP: HCQU-Main | MyODP (https://www.myodp.org/mod/page/view.php?id=7699)
– Course: 2024 – Dual Diagnosis Curriculum | MyODP (https://www.myodp.org/course/view.php?id=2390)
– Resources – Office of Mental Health and Substance Abuse Services (https://myomhsas.org/category/communications/resources/)
– HEAL PA (https://www.healpa.org/)
– Wellness Recover Action Plan (WRAP) https://www.wellnessrecoveryactionplan.com/
Note: The measure does include training/activities for individuals as well as staff.
The following crisis prevention and de-escalation training programs meet measure CN-DD/Bx.03.4:
a. Ukeru
b. Crisis Prevention Institute (CPI)
c. Collaborative and Protective Solutions (CPS)
d. Mandt System®
e. Non-Violent Crisis Intervention Training
f. Therapeutic Options
g. Safe and Positive Practices/Approaches
h. Quality Behavioral Solutions (QBS) – Safety Care
i. Welle – Kurk Lalemand
j. Safe Crisis Management (SCM)
k. Comprehensive Crisis Management (“CCM”) Training Program – UPMC
NOTE: “Positive Behavioral Interventions and Supports (PBIS)” was removed from the original list because PBIS is an approach to behavioral intervention and not a curriculum. One cannot get liability coverage through PBIS nor can one be certified in PBIS in the same way these can be accomplished in other curricula listed.
Yes. Providers must demonstrate the appropriate capacity to serve individuals with complex medical needs AND complex behavioral needs if they would like to be considered for Clinically Enhanced – Both.
Performance Measures: Data Management
The requirement to have an Electronic Health Record applies to Life Sharing and Supported Living providers in the Select or Clinically Enhanced Tiers. ODP allows agency use of electronic medication administration records to meet the minimum standard. Electronic medication administration records are often web-based, cloud services that can be accessed from any device that supports a web-browser such as a computer, laptop, or mobile-device, and would be used as appropriate to meet the support needs of the individual receiving residential services.
Electronic medication administration records are not required to be used for every individual receiving residential services. The residential provider must have electronic medication administration records available to support individuals and residential direct support professionals in achieving outcomes related to appropriate medication administration.
ODP expects that Electronic Health Records will be available for use by all individuals who receive residential services and deployment is person centered.
Please see Deputy Ahrens’ October 15, 2025 letter.
Performance Measures: Regulatory Compliance
In previous PBC cycles, measure RC.01 was met if the provider was on regular license status (i.e., not operating under a provisional, revoked, or nonrenewed license at any residential homes). Beginning in this cycle, providers must be on regular license status and may not be subject to any sanction specified in Chapter 6100. Information about Chapter 6100 sanctions can be found at 55.Pa Code § 6100.741 – § 6100.744.
Performance Measures: Risk Management
Providers can access their data for RM.IM.01.2 and RM.IM.01.4, through the Enterprise Incident Management dashboard. ODP recommends reviewing the Guidance for Reviewing Data for PBC Measures RM-IM.01.2-0.1.3 -.01.4 pdf for more information.
ODP will publish status by MPI for RM-IM.01.1 – 01.4.
The provider will receive notification about an unreported incident from the applicable Administrative Entity. This number divided by the total number of Provider Type 52 incidents submitted during the time period under review will produce the percent of unreported incidents.
If a provider that submitted for Select or Clinically Enhanced receives notification that this measure was not met during ODP’s assessment for tier determination, the provider may use the PBC Resolution Process to demonstrate using their own records what they believe the actual percentage to be. ODP will then review the submission to determine if the tier determination should be changed.
The discovery date is the date and time that an initial reporter became aware of, or suspected that, a reportable incident occurred.
The occurrence dates and discovery dates can be different.
For regulatory compliance and for PBC measures, ODP relies only on the discovery date and time as that determines when the first section of a report must be submitted.
Performance Measures: Workforce
NADSP Certification (DSP-I, DSP-II, DSP-III, FLS) requires recertification every two years. By the end of the two-year term, the certified DSP or FLS must complete/submit at least 20 hours of training. This training does not have to be NADSP-Accredited, but no more than 8 of the 20 hours can be from mandatory training requirements. (Certification Renewal Application (DSP I, DSP II, DSP III, FLS) – NADSP)
If a provider had 20 credentialed DSPs out of 200 DSPs on 1/1/2026, that would equal 10% credentialed DSPs. For this calculation, we are counting the persons rather than the number of credentials, as one person can have multiple credentials. Both the numerator and denominator are from 1/1/2026.
If the total number of DSPs increases to 220 on 12/31/2026, the provider would need to have 27 or more credentialed DSPs by 12/31/2026. That’s 7 newly credentialed DSPs. Both the numerator and denominator are from 12/31/2026.
20/200 = 10% to 27/220 = 12% is a 2-percentage point increase.
If a provider had 20 credentialed DSPs out of 200 DSPs on 1/1/2026, that would equal 10% credentialed DSPs. For this calculation, we are counting the persons rather than the number of credentials, as one person can have multiple credentials. Both the numerator and denominator are from 1/1/2026.
If the total number of DSPs increases to 220 on 12/31/2026, the provider would need to have 33 or more credentialed DSPs by 12/31/2025. That’s 13 newly credentialed DSPs. Both the numerator and denominator are from 12/31/2026.
20/200 = 10% to 33/220 = 15% is a 5-percentage point increase.
Note: Providers having greater than 25% of DSPs credentialed are considered to meet the standard without the requirement to increase the percentage.
The NCI portal will open in February of each year. While we understand that this is a short amount of time to complete the survey, the requirement will remain participation in the most recent NCI State of the Workforce survey.
Providers should click on the original link in the invitation email they used to access the survey. If the survey was completed, providers will be brought to this page:

Providers can click on “Review”, then scroll to the bottom of the page to see an option to “PRINT” the responses. This will allow providers to download their responses as a PDF.
Pay for Performance Initiatives
Please review the Rural Capacity P4P Operational Guide.